
How to Tell If Your Baby Has a Tongue or Lip Tie (And What Actually Happens at an Evaluation)
If you've found yourself Googling this at 2am with a baby latched (or unlatched, again, for the fifth time tonight), you're not alone, and you're not imagining things. Tongue and lip ties are common, often missed, and surrounded by a lot of conflicting information online. Some of it will scare you. Some of it will dismiss you. Our goal here is neither, just a clear, honest look at what to watch for, and what actually happens at a tongue tie assessment and diagnosis, from a Bowling Green, KY tongue tie specialist's perspective.
What a Tongue or Lip Tie Actually Is
A tongue-tie (ankyloglossia) happens when the strip of tissue connecting the tongue to the floor of the mouth is tighter or shorter than typical, limiting how freely the tongue can move. A lip-tie is the same idea, but with the tissue connecting the upper lip to the gum. Neither is rare but neither always causes a problem, either. The tissue itself isn't the diagnosis. What matters is function: can your baby's tongue and lips move the way they need to for an effective, comfortable feed?
That distinction matters more than it might seem. It's the difference between a provider who looks and says "yep, that's tied, let's release it" and one who actually assesses whether the tie is affecting feeding at all.
Signs Worth Paying Attention To
No single sign confirms a tie on its own, but if several of these sound familiar, it's worth having a real evaluation:
- Painful latch that doesn't improve even after working on positioning
- Clicking or smacking sounds during feeding, which often means baby is losing suction
- Falling asleep quickly at the breast or bottle but waking hungry soon after: a sign they may be working hard without transferring much milk
- Poor weight gain, or a baby who feeds constantly but never seems satisfied
- Milk supply dropping over time, since an ineffective latch removes less milk and can slowly signal your body to make less
- Gassiness, reflux-like symptoms, or a lot of air intake during feeds
- Bottle refusal or gagging, especially with certain nipple shapes
If you're nodding along to a few of these, remember that's just information (not a diagnosis) and not a reason to panic. It's a reason to get a real look.
What Actually Happens at a Functional Oral Assessment
This is the part that tends to get skipped in a lot of online advice, and it's the part that matters most. A thorough evaluation isn't a quick glance in the mouth. It's a full picture of how your baby feeds.
We start by listening. Your feeding history, what's been worrying you, what you've already tried. You know your baby better than a five minute exam ever could, and that history shapes everything that comes next.
Then, a hands on look at oral function: how your baby's tongue, lips, and cheeks move and coordinate, not just what the tissue looks like at rest. A tie can look dramatic and cause no functional issue, or look subtle and be significantly limiting movement. Appearance alone doesn't tell the story.
Real-time feeding observation and troubleshooting. Watching an actual feed, breast or bottle, to see how everything works together in practice, and trying adjustments to latch and positioning before assuming a release is the answer.
A weighted feed, when appropriate, to see objectively how much milk your baby is actually transferring…not a guess, an actual number.
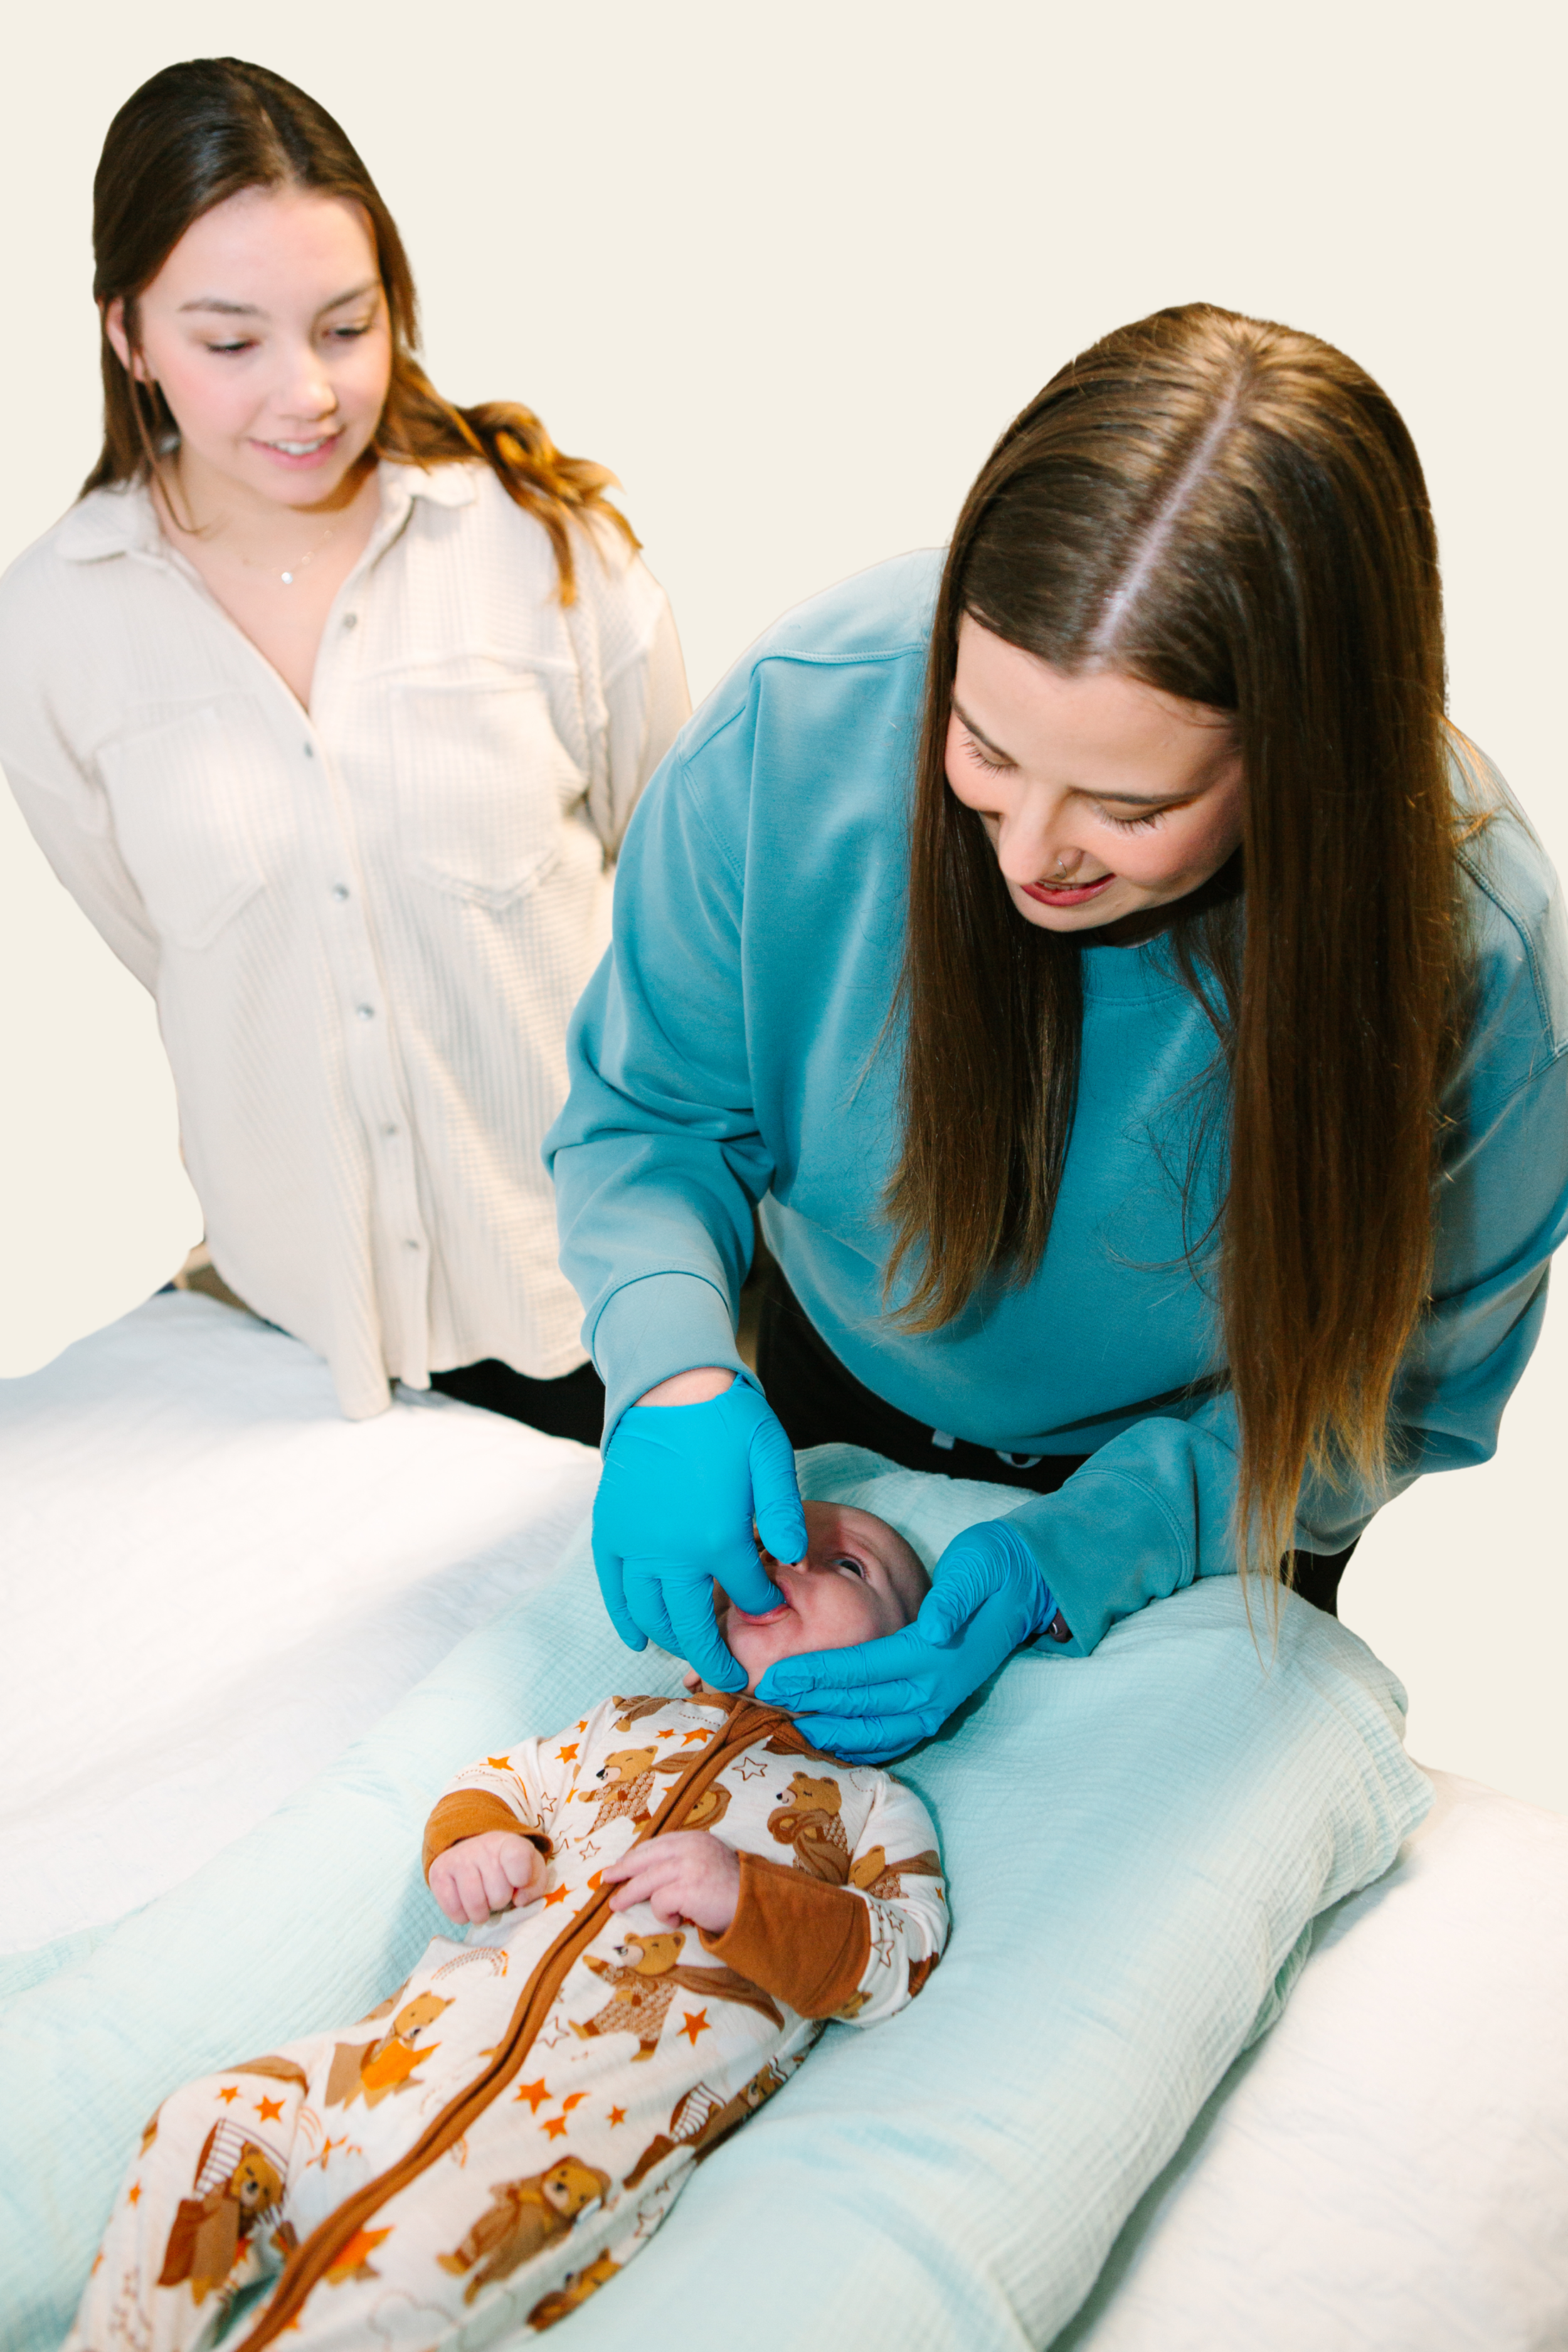
This is what a real functional oral assessment looks like. Not a quick glance, a genuine, hands-on look at how baby's mouth actually moves and works.
Red Flags to Watch For in a Tongue-Tie Evaluation
Not every provider evaluating for tongue and lip ties is doing so thoroughly and because this is a fast-growing, often rushed corner of care, it's worth knowing what a lack of due diligence looks like before you're standing in the room making a decision about your baby's mouth that has lifelong impacts.
1) There's no separation between who assesses and who treats. If the same person who evaluates your baby for a tie is also the one performing the release, with no outside check, no second set of eyes, no referral process, there's no built-in accountability in that recommendation. A pediatric dentist performing a release after being referred by an IBCLC is a normal, appropriate structure. A single provider (pediatrician, midwife, APRN, etc) doing both the diagnosing and the surgical release, as standard practice, removes an important checks and balances step that protects your baby from an unnecessary procedure.
2) The assessment is quick. A genuinely thorough functional oral assessment, looking at your baby's whole-body tension patterns, oral reflexes, and actual feeding mechanics, not just a glance at the tissue, typically takes 30 to 45 minutes. If the entire evaluation is over in a few minutes, it likely isn't assessing function at all…just appearance.
3) Your baby doesn't get watched feeding. A tie can only be properly understood in the context of how it's actually affecting feeding. If no one observes a real feed, breast or bottlem before a recommendation is made, that recommendation isn't based on your baby's actual feeding, just on what the tissue looks like. That recommendation isn't based on function, it's based on appearance alone, and appearance alone isn't enough.
4) There's no attempt to improve the feed first. Exercises, bodywork, positioning changes, and feeding adjustments should be tried before release is presented as the answer and a good provider gives you exercises for both body and mouth to work on, and helps you make real progress on the feed itself, before a frenectomy ever enters the conversation.
A good evaluation should be just as willing to tell you a release isn't needed as it is to tell you it is. If any of the above sounds like what you experienced, it's absolutely worth getting a second opinion before moving forward with a procedure on your baby's mouth.
If a Release Is Recommended
A frenectomy isn't the end of the process. It's just the start of a recovery period that requires guided aftercare: stretches to prevent the tissue from reattaching too tightly, oral habilitation exercises to teach the new mouth how to work, and continued support adjusting to a new range of motion. Post-release care matters just as much as the release itself for a good outcome.
The Bottom Line
Tongue and lip ties are real, common, and worth taking seriously, but they're not something to diagnose from a photo on the internet, and they're not something that should be treated as an automatic yes just because the tissue is visible. What matters is a real, functional assessment of how your baby is actually feeding, done by someone with genuine, ongoing training in this specific area, not a quick look and a recommendation either way.
If any of this sounds familiar, we'd be glad to help you get real answers. As a Bowling Green, KY tongue tie specialist, Emily offers thorough tongue tie assessment, whether you're able to come in or need to connect virtually (a full functional evaluation using the same clinical criteria, wherever you are), and when a release is genuinely needed, guidance through tongue tie release from start to finish. Learn more about our Functional Oral Assessment & Tongue-Tie Evaluation visits → here.
---
Emily has completed advanced training through Oral Habilitation of the Breastfeeding Dyad: A Masterclass for the IBCLC, is TOTS® (Tethered Oral Tissues Specialty) Trained, is Master Reflexive™ Oral Function trained, and is a yearly attendee of the GOLD Tongue-Tie Symposium, just to name a few, bringing ongoing, current expertise in tongue-tie evaluation and care.
